
Doctors
From barber-surgeons to university physicians
By Isabelle Devos
Today, doctors are highly trained professionals at the heart of our healthcare system. In 19th-century Belgium, however, they were only one group among many providing medical care. Patients might also turn to (barber-)surgeons or informal healers. Over time, university education, state regulation, and new scientific knowledge strengthened the position of doctors. Their numbers grew, and they gradually became more widely available across the country.
Image:
In early 19th-century Belgium, medical care was provided by a wide range of practitioners. University-trained physicians generally enjoyed the highest professional status. They diagnosed illnesses, prescribed medicines and advised patients, but performed few of the manual procedures. Surgeons, on the other hand, had learned their skills through practical training and apprenticeships rather than at university. They treated wounds, performed bloodletting, extracted teeth and carried out operations such as amputations.
Alongside these recognised practitioners were numerous informal healers. Medical authorities often dismissed them as quacks. They offered herbal remedies, traditional cures and other forms of treatment sometimes based on magic or superstition. Such healers remained popular, particularly in rural areas, where they were often cheaper and more accessible than formally trained medical practitioners.
Figure 1: The quack in the village

The term “barber-surgeon” dates back to medieval Europe, when barbers did more than cut hair and trim beards. Because they were skilled with razors and other sharp instruments, some also performed practical medical procedures such as bloodletting, tooth extraction, wound treatment and even amputations.
The word “surgeon” comes from the Greek cheirourgos (“working with the hands”), while barber derives from the Latin barba (“beard”). Over time, surgery developed into a distinct medical profession, increasingly separated from the barber’s trade.
During the 19th century, the government gradually brought this diverse medical world under greater control. From 1831 onwards, new regulations reduced the distinction between physicians and surgeons, eventually bringing them together within a single medical profession. Universities were given full responsibility for medical education in 1835, which was modernised and made more practice oriented. University training for pharmacists followed in 1849, and dentists in 1884.
The effects were important. Around 1830, only about 48% of physicians had received university training. By 1880, the figure had risen to around 80%. At the same time, the authorities increasingly restricted quackery, although informal healers never disappeared entirely.
More doctors, but not everywhere
Figure 2:
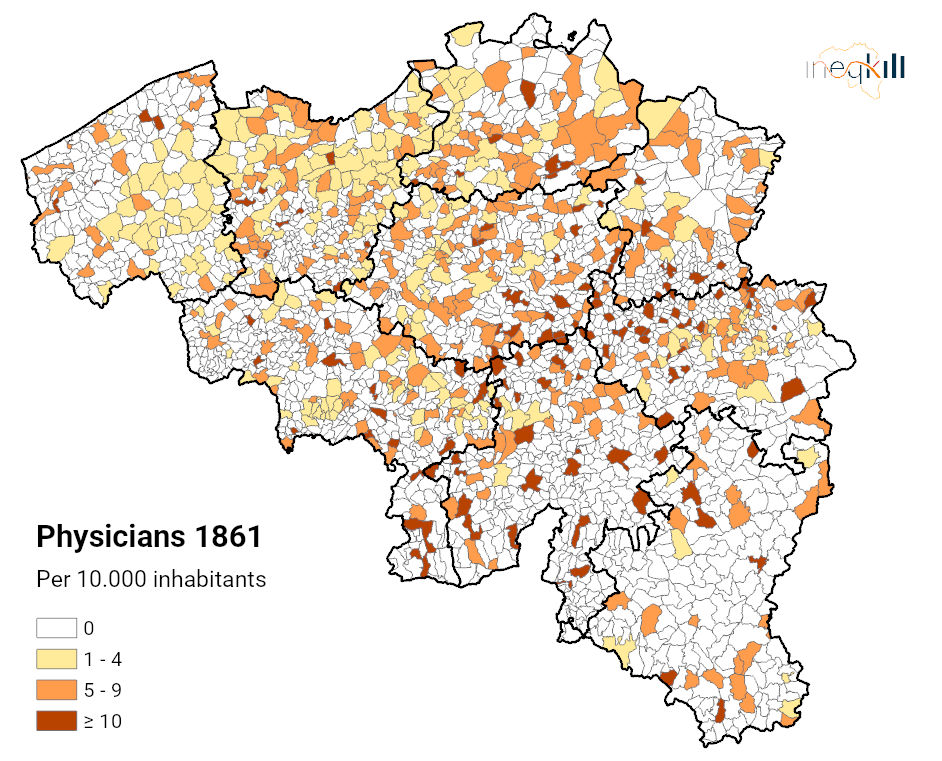
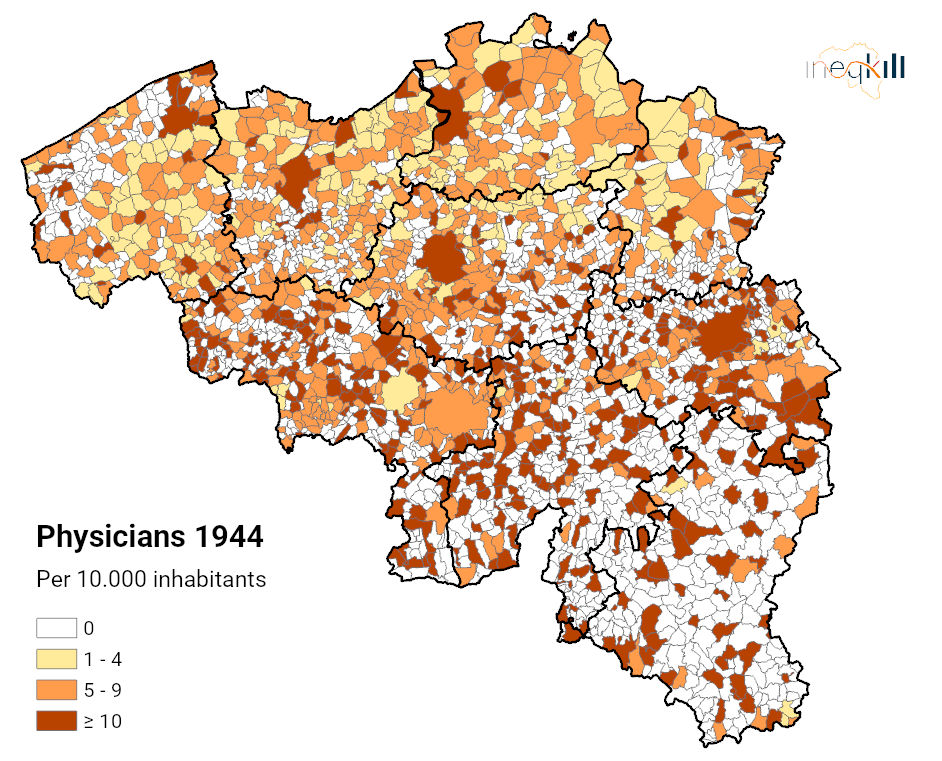
Better training did not mean that everyone suddenly had access to a doctor. Far from it. In 1861, according to the Annuaire médical de la Belgique, an administrative medical report, about 70% of Belgium’s 2,538 municipalities had no resident physician or surgeon. Doctors were particularly scarce in coastal Flanders and southern Belgium (the Ardennes) (Figure 2a). There was a simple economic reason for this. In sparsely populated rural areas, patients lived far apart and many could not afford to pay for medical care. For a doctor trying to make a living, setting up a practice there was often unattractive.
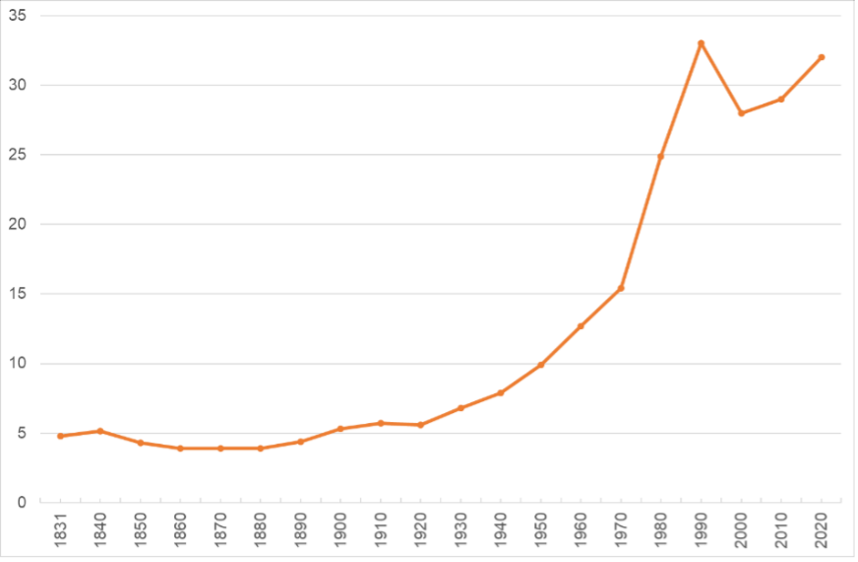
Nor did the number of doctors rise steadily throughout the 19th century (see Figure 3). Belgium had about 5 doctors for every 10,000 inhabitants in the 1830s and 1840s. Between 1850 and 1880, that figure actually fell to around 4, partly because stricter training requirements made it more difficult to enter the profession. From the 1890s onwards, the trend changed. Medical education expanded, and more doctors began to specialise.
By the middle of the 20th century, Belgium had around 10 doctors for every 10,000 inhabitants, roughly twice as many as a century earlier. They were also distributed more evenly across the country (see Figure 2b). The largest concentrations were still found in and around cities such as Antwerp, Brussels, Ghent and Liège, but smaller towns and rural areas were catching up. Regional differences nevertheless persisted. Parts of Flanders and the Ardennes continued to have fewer doctors, reflecting differences in population density, accessibility and wealth.
Figure 3: Number of physicians per 10,000 inhabitants
Belgium, 1831 -2020
Healthcare becomes more accessible
Figure 4
After the Second World War, access to healthcare expanded much more rapidly. The welfare state grew, compulsory health insurance was introduced and governments invested heavily in hospitals and other medical services. Seeing a doctor became affordable for a much larger share of the population. Medicine itself was also becoming more effective. Antibiotics, for example, made it possible to treat infections that had previously killed large numbers of people. As doctors became more capable of actually curing disease, public confidence in professional medicine grew.
The number of doctors rose rapidly as well. By 1990, Belgium had around 33 doctors per 10,000 inhabitants. This rapid expansion eventually raised concerns about an oversupply of doctors and its possible effects on doctors’ incomes and professional status. In the late 1990s, Belgium therefore introduced restrictions on the number of students entering medical training (numerus clausus).
How often did people actually see a doctor?
Having doctors nearby is one thing. Going to see one is another. In the 19th century, most people consulted doctors far less often than we do today. Professional medical care was expensive, and many people, especially among the rural and working-class population, continued to rely on family knowledge, home remedies and local healers.
There was also good reason to be sceptical about what doctors could offer. Before the 20th century, their ability to diagnose and treat disease was limited. There were no blood tests, X-rays or modern laboratory tests. Doctors largely depended on what they could see, hear and feel: they observed their patients, took their pulse, examined their tongue and listened to descriptions of their symptoms. Many treatments were based on older ideas about the balance of the body’s “humours”. Bloodletting, cupping, purging, lancing and herbal remedies were common. Medicines such as opium, quinine, morphine and alcohol were also widely used. Some treatments helped, but others were ineffective or could even make patients worse.
And seeing a doctor was expensive. There was no general health insurance, so patients normally had to pay the full cost themselves. In the 19th century, a simple consultation could cost almost an entire day’s wages for a worker, and medicines had to be paid for separately. Not surprisingly, people often waited until an illness became serious before calling a doctor. Preventive check-ups and routine follow-up visits were rare. Household budgets suggest that people averaged only around one medical consultation every two years during the 19th century. Around 1900, this had increased to nearly 1 consultation per person per year.
From the late 19th century onwards, medical care gradually became more affordable. Yet even around the middle of the 20th century, a doctor’s visit could still cost roughly half a day’s wages. Since then, the relative cost has fallen dramatically. Today, the full price of a consultation is around 15% of a day’s wage. For an insured patient, the amount paid out of pocket is closer to 1.5%.
Figure 5: The doctor's visit

Who could afford medical care?
Access to healthcare did not simply divide society into rich people who could afford doctors and poor people who could not. The reality was more complicated. Paradoxically, the very poorest sometimes had better access to medical care than people who earned just enough to receive no public assistance, but too little to comfortably pay a doctor themselves.
Care for the poor was not new in the 19th century. Since medieval times, hospitals, religious institutions, charitable foundations and local communities had provided assistance to people who could not support themselves, including care for the sick. What changed during the 19th century was the scale and organisation of this assistance. Medical care for the poor became increasingly formalised and integrated into local public welfare, including preventive measures such as smallpox vaccination.
These policies were not motivated by compassion alone. Epidemics made clear that infectious diseases did not respect social boundaries. During cholera outbreaks, for example, providing care to poorer neighbourhoods was also seen as a way of protecting the rest of society.
In Belgian towns, many poor people therefore had access to some form of medical assistance. Local welfare boards employed physicians— often known as “doctors of the poor”—to provide free consultations and basic treatment, visit patients at home and monitor sanitary conditions in poorer neighbourhoods. Hospitals and hospices also reserved beds for people unable to pay.
Figure 6: Doctor for the poor

Workers organise their own healthcare
Workers had also organised forms of mutual support long before the 19th century. In the early modern period, many guilds and other occupational associations collected contributions from their members and could provide financial assistance in times of sickness, disability or death. These arrangements were limited to particular groups, but they established a long tradition of sharing the risks of illness.
During the 19th century, this tradition took on new forms. As the old guild system disappeared and industrialisation transformed the world of work, workers established mutual aid societies. Members paid regular contributions to sickness funds, which helped cover medical treatment and medicines and sometimes provided an income when illness or disability prevented them from working.
The Belgian government officially recognised mutual societies in 1851. A new law in 1898 provided subsidies to recognised societies and encouraged their rapid expansion. In 1875, Belgium had 137 recognised mutual societies. By 1911, there were 3,299, with more than half a million members. Catholic and socialist organisations both played an important role in this expansion.
Together, these mutual societies helped lay the foundations of Belgium’s modern health insurance system. Government legislation gradually added further protection, including workplace safety regulations, compensation for industrial accidents and access to specialised medical care.
Figure 7: Evolution of health insurance in Belgium

Towards healthcare as a social right
By the early 20th century, medical care had become more widely available, but important inequalities remained, particularly in rural areas. The wealthiest groups had long enjoyed advantages of a different kind. They could pay for private doctors and were among the first to benefit from medical specialists and private clinics.
The decisive change came after the Second World War. Compulsory health and disability insurance was introduced for employees in 1945 and extended to the self-employed and civil servants in 1964. Over little more than a century, Belgium had moved from a world in which access to qualified medical care depended heavily on where you lived and what you could afford towards one in which healthcare was increasingly regarded as a social right for everyone.
Want to read more?
- Havelange, Carl. Les figures de la guérison. XVIIIe–XIXe siècles : une histoire sociale et culturelle des professions médicales au pays de Liège. Liège, 1990.
- Meul, Ineke, en Rita Schepers. “De opkomst en consolidering van medische specialisten in België (1857–1957).” Belgisch Tijdschrift voor Nieuwste Geschiedenis 43, nr. 1 (2013): 10–45.
- Schepers, Rita. De opkomst van het medisch beroep in België. De evolutie van de wetgeving en de beroepsorganisaties in de 19e eeuw. Leiden: Brill, 1989.
- Vandenbroeke, Chris. “De medische consumptie sinds de 16de eeuw.” Handelingen der Maatschappij voor Geschiedenis en Oudheidkunde te Gent 34, nr. 1 (1980): 143–165.
- Velle, Karel. De nieuwe biechtvaders. De sociale geschiedenis van de arts in België. Leuven, 1991.
- Velle, Karel. “Medikalisering in België in historisch perspektief: een inleiding.” Belgisch Tijdschrift voor Filologie en Geschiedenis / Revue belge de philologie et d’histoire 64, nr. 2 (1986): 256–285.
Sources
- Annuaire médical de la Belgique 1861
- Annuaire de la Santé publique 1944